
Anagen effluvium
When a powerful treatment, toxin, or medical event disrupts actively growing follicles, hair can become fragile and shed rapidly—often within days to a few weeks.
Educational guide · Never change chemotherapy or another essential medicine without the prescribing team

What is anagen effluvium?
Anagen effluvium is sudden hair loss caused by disruption of hairs during their active growth phase.
- Hair may narrow, weaken, and break close to the scalp.
- Chemotherapy is the best-known cause, but it is not the only one.
- Scalp, facial, and body hair can be affected.
Rapid onset separates it from delayed shedding.
Link the onset to recent treatment or exposure, but do not assume that timing alone establishes the diagnosis.
Day 0
A cytotoxic treatment or other major insult affects rapidly dividing cells in the hair bulb.
Days
Newly forming shafts can narrow and weaken while hairs are still in active growth.
About 1–3 weeks
Fragile hairs may break near the scalp or shed in large amounts. Timing varies.
Following months
When follicles recover, new growth may begin; density, texture, and color can temporarily differ.
Growing shafts are abruptly disrupted.
Resting club hairs release after a delay.
The hair shaft weakens while it is being formed.
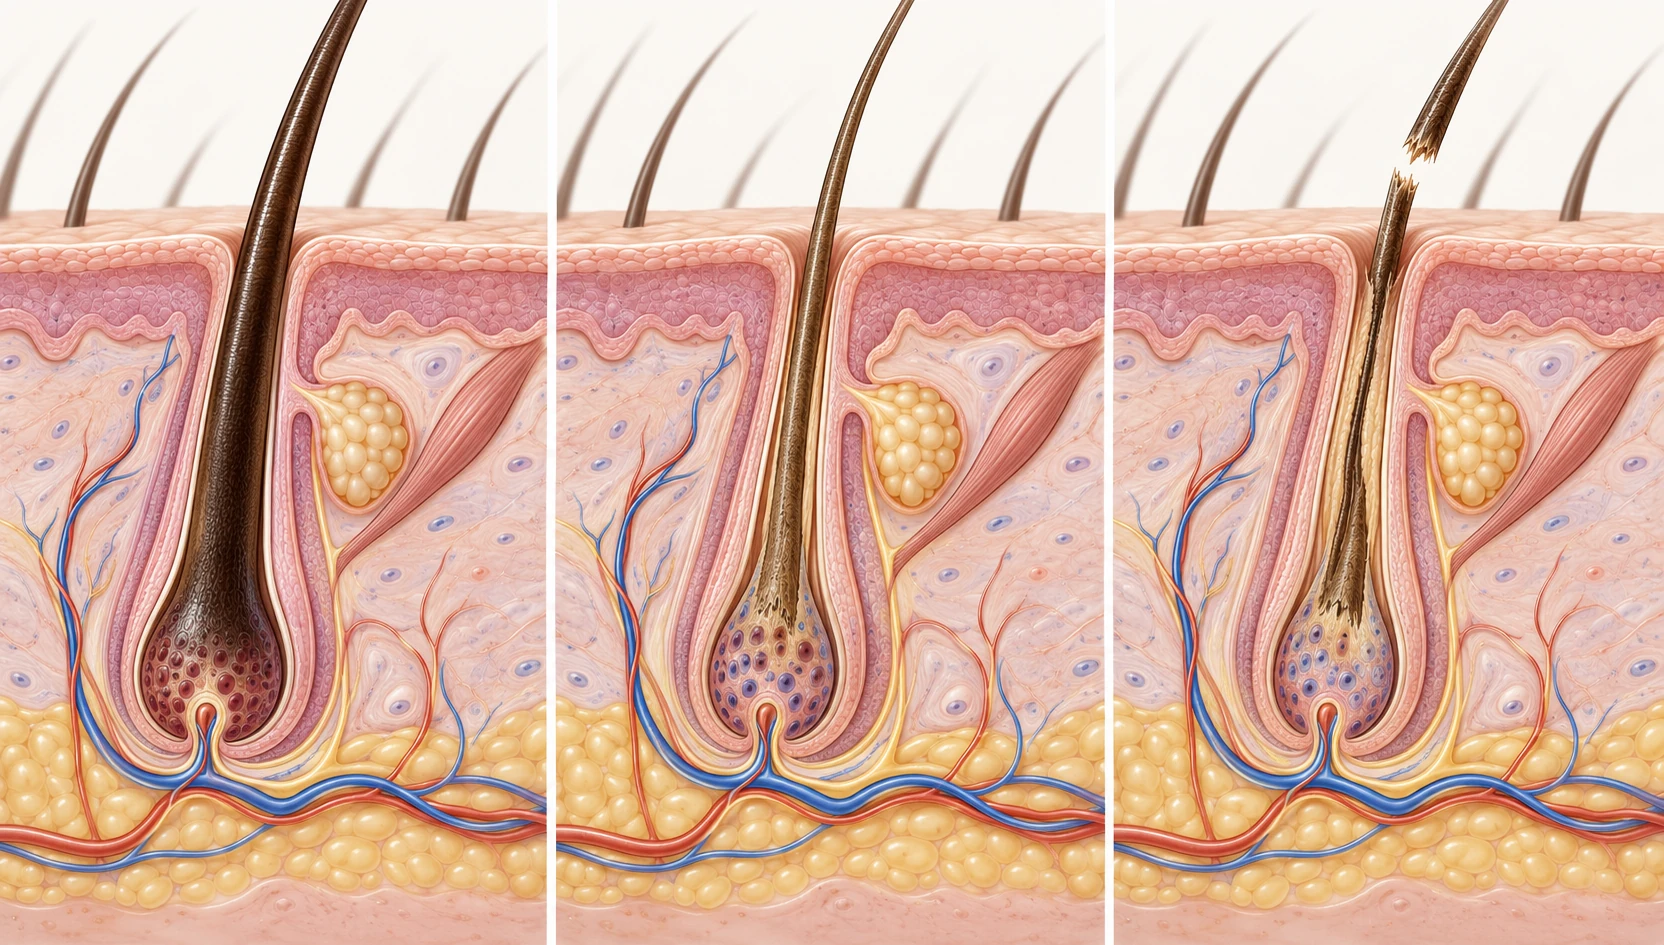 EDUCATIONAL FOLLICLE CROSS-SECTION
Active growth
Matrix cells in the bulb divide rapidly to build a strong, pigmented shaft.
Growth is disrupted
The forming shaft narrows or becomes structurally fragile.
The shaft breaks
A dystrophic hair may fracture near the scalp while the follicular opening remains.
Anything that abruptly disrupts rapidly dividing follicle cells can be relevant.
The cause determines the medical priority, expected course, and whether any preventive option is appropriate.
Cytotoxic chemotherapy
The most recognized cause. Risk, timing, and severity vary substantially by medication, dose, combination, and schedule.
Radiation exposure
Radiation can affect follicles within the treated field; regrowth depends partly on dose and tissue response.
Toxic exposures
Heavy metals and other toxins can damage actively growing hairs and may require urgent medical investigation.
Other severe follicle disruption
Certain medicines and inflammatory or systemic conditions can produce rapid dystrophic shedding and need clinician-led evaluation.
The loss can be dramatic even when the scalp looks relatively normal.
Sudden heavy loss
Large amounts may appear in the shower, brush, on bedding, or with gentle handling.
Short broken hairs
Fragile shafts can snap close to the scalp rather than release as intact club hairs.
Widespread involvement
Density may fall across much of the scalp and sometimes the brows, lashes, or body.
Preserved openings
The scalp is usually non-scarring, without the smooth loss of follicular openings seen in cicatricial alopecia.
The recent medical timeline often provides the strongest clue.
Review treatments and exposures
Document new medicines, chemotherapy agents and dates, radiation fields, occupational exposure, and acute illness.
Examine scalp and shed hairs
Trichoscopy and microscopy can show broken, tapered, narrowed, or dystrophic anagen hairs.
Investigate when unclear
Targeted blood tests, toxicology, or biopsy may be appropriate when no expected trigger explains rapid loss.
When shedding occurs during cancer therapy or treatment of a serious illness, hair-loss advice should be coordinated with the relevant medical specialists. Do not interrupt essential treatment independently.
Not every sudden shed is anagen effluvium.
Telogen effluvium
Usually appears 90–120 days after a trigger and releases resting club hairs.
Alopecia areata
Can produce rapid patchy or diffuse loss through immune-mediated follicle disruption.
Hair breakage
Chemical, heat, or mechanical damage affects the shaft and may resemble short dystrophic loss.
Protect the medical priority while supporting the person and scalp.
The correct plan depends on the cause. Hair preservation should never compromise necessary treatment.
Address the trigger safely
Remove a toxin or reconsider a nonessential medicine only under appropriate medical direction.
Do not self-discontinue treatmentAsk about scalp cooling
For selected chemotherapy regimens, the oncology team may discuss whether scalp cooling is suitable.
Benefits and eligibility varyUse gentle scalp care
Reduce friction, harsh chemicals, tight styling, and high heat while shafts and scalp are vulnerable.
Comfort and breakage reductionPlan supportive options
Shorter styling, scarves, hats, wigs, prostheses, and counseling can provide practical and emotional support.
Personal choice mattersNo product can guarantee prevention or regrowth. Scalp cooling, prescriptions, and changes to medically necessary treatment require the responsible licensed clinical team.

New growth may return differently at first.
After the follicle resumes production, early hair may differ in texture, curl, color, or thickness. Regrowth timing and completeness vary; repeated or high-intensity exposure can sometimes cause lasting reduction.
Track progress with consistent photographs—not day-to-day impressions.Unexpected rapid loss deserves an explanation.
Contact the treating team for sudden loss without an expected trigger, possible toxin or heavy-metal exposure, scalp pain or inflammation, neurological or gastrointestinal symptoms, or shedding that continues well beyond the anticipated treatment window.
Do not delay urgent medical care while pursuing cosmetic or hair-growth treatment.
Anagen effluvium, clearly explained.
How quickly does anagen effluvium begin?+
It can become noticeable within days to a few weeks after a major trigger. With chemotherapy, shedding commonly begins around one to three weeks after treatment starts, although timing varies by drug and regimen.
Is anagen effluvium permanent?+
It is often temporary because the follicle usually remains present. Regrowth depends on the trigger, dose, duration, and individual response; some intensive or repeated treatments can cause incomplete or permanent loss.
Does it affect only scalp hair?+
No. Because actively growing follicles are affected, eyebrows, eyelashes, facial hair, and body hair may also shed.
How is it different from telogen effluvium?+
Anagen effluvium begins rapidly because growing hairs are damaged. Telogen effluvium is delayed—usually becoming visible about 90 to 120 days after a trigger—and typically releases club hairs from the resting phase.
Can scalp cooling prevent chemotherapy hair loss?+
Scalp cooling may reduce hair loss with some chemotherapy regimens, but it is not suitable or effective for everyone. The oncology team should determine whether it is appropriate and safe.
Should cancer treatment be stopped because hair is shedding?+
Do not stop or change cancer treatment because of hair loss without speaking with the oncology team. Hair preservation decisions must remain secondary to safe, effective treatment of the underlying disease.
Medical review notes
This guide preserves the existing Trichology.com foundation—growth-cycle disruption, chemotherapy, radiation, toxins, diagnosis, and regrowth—while making the rapid timeline and care boundaries clearer.
Medical disclaimer: This content is educational and is not a diagnosis or substitute for care from a qualified health professional.
Compare rapid growth-phase loss with delayed shedding.
The timing, shed-hair shape, and recent treatment history help separate these conditions.