
Alopecia areata
A smooth patch that seems to appear suddenly can be unsettling. Alopecia areata occurs when immune activity interrupts hair growth—and it can affect the scalp, face, or body in several distinct patterns.
Educational guide · A photograph alone cannot confirm alopecia areata
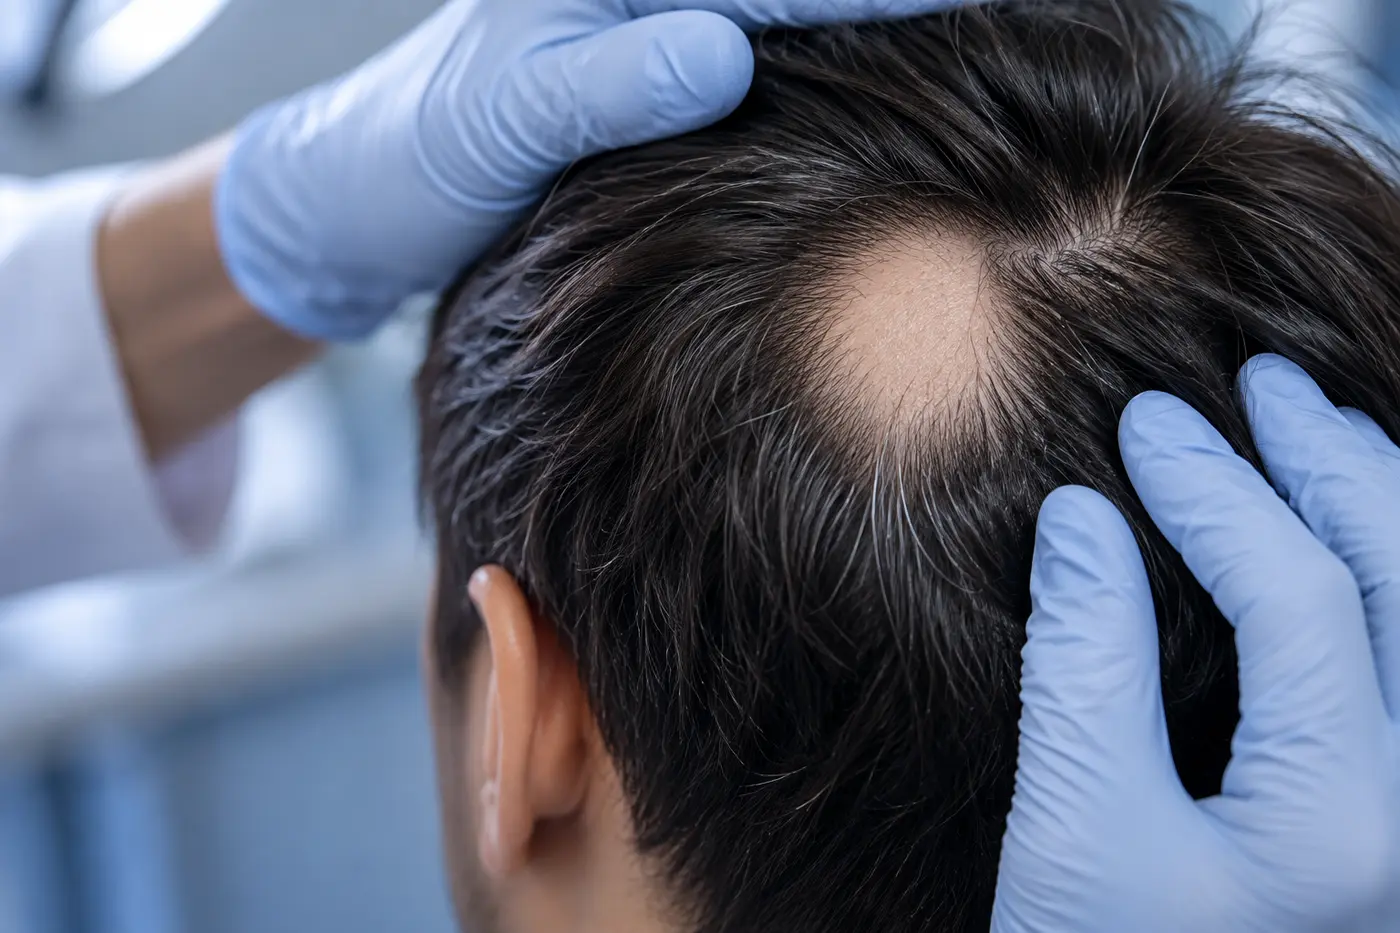
What is alopecia areata?
Alopecia areata is an autoimmune hair-loss disorder. Immune cells mistakenly target growing follicles, causing hair to release—most often in sudden, smooth patches.
- It can begin at any age and affect any sex or ethnicity.
- It is not contagious and is not caused by poor hair care.
- Its course is individual: regrowth and recurrence are both possible.
The skin often looks normal even though the hair loss is sudden.
The pattern may be obvious, subtle, or diffuse. These visual clues guide an assessment but do not establish the diagnosis.
Smooth patches
One or more round or oval areas can appear over days or weeks.
Edge activity
Short tapered “exclamation-point” hairs, broken hairs, or black dots may appear near an active patch.
Face or body hair
Eyebrows, eyelashes, beard hair, and other body hair may also be involved.
Nail changes
Fine pits, ridges, roughness, or brittle nails can accompany the condition.
Redness, heavy scale, pustules, crusting, pain, or loss of follicle openings is not the classic presentation and should prompt evaluation for another inflammatory or scarring process.
See how alopecia areata can change in distribution and severity.
The images illustrate common presentations. Real cases vary, and the extent seen in a photograph does not predict an individual person’s future course.
 01
Patchy alopecia areata
One or more sudden, smooth, round or oval areas of hair loss.
 02
Diffuse alopecia areata
More widespread thinning or shedding without the classic isolated patches.
 03
Alopecia totalis
Complete or nearly complete loss of hair from the scalp, while facial hair may remain.
 04
Alopecia universalis
Complete or nearly complete loss of scalp, facial, and body hair.
Patchy, diffuse, totalis, and universalis describe different distributions—not a guaranteed step-by-step progression. Other recognized patterns include ophiasis, which follows a band around the lower sides and back of the scalp.
Hair follicles and nails can show signs of the same immune activity.
Nail changes can appear before, during, or after hair loss and may involve one nail, several nails, or—in trachyonychia—many fingernails and toenails.

Fine pitting
Tiny, shallow pinpoint depressions scattered across the nail plate. Alopecia areata pits are often fine and regularly distributed.

Trachyonychia
A rough, dull, sandpaper-like surface with many fine longitudinal ridges. Nails may also become thin, brittle, or fragile.

Leukonychia
Small white spots or short white streaks within the nail plate. This finding has many possible causes and is not specific to alopecia areata.

Red-spotted lunula
Small red dots within the pale half-moon at the nail base. This is a recognized but uncommon finding.
Pitting, ridging, brittleness, and white spots also occur with psoriasis, eczema, lichen planus, fungal infection, trauma, aging, and other conditions. Nail findings may support an alopecia areata assessment, but they cannot confirm it independently. Pain, swelling, drainage, separation, or a dark changing streak deserves medical evaluation.
The immune system disrupts the follicle’s normal growth activity.
Susceptibility
Genetic and immune factors can increase risk. Many people have no family history.
Immune attack
Inflammation forms around actively growing follicles and interrupts anagen growth.
Hair release
Hair sheds or breaks while the follicle structure is usually preserved beneath the skin.
Possible regrowth
When immune activity settles or responds to treatment, follicles may resume growth.
Illness or emotional stress may precede an episode in some people, but they do not explain every case. Alopecia areata reflects autoimmune susceptibility—not a personal failure to manage stress.
Diagnosis starts with the pattern, the scalp, and the wider health picture.
History and distribution
Timing, recurrence, family history, scalp and body-hair involvement, nail changes, medications, and other symptoms.
Close examination
A dermatologist may use magnification to look for tapered hairs, black dots, broken hairs, regrowth, inflammation, and preserved follicle openings.
Tests when indicated
A biopsy or targeted blood testing may be used when the diagnosis is uncertain or the history suggests another condition.
Alopecia areata can coexist with androgenetic alopecia or telogen effluvium. Thyroid disease, vitiligo, psoriasis, eczema, and other immune or allergic conditions may be more common, but testing should be guided by the individual history.
Not every patch of hair loss is alopecia areata.
Tinea capitis
Fungal infection may produce scale, broken hairs, inflammation, or tender areas and needs medical treatment.
Traction or hair pulling
Mechanical loss often follows hairstyle tension or shows irregular hairs of different lengths.
Scarring alopecia
Burning, scale, redness, pustules, or smooth shiny areas can signal permanent follicle injury.
Treatment depends on age, extent, duration, activity, and personal goals.
There is no single treatment plan for every person. A dermatologist should explain the expected benefit, limitations, monitoring, and risks of each option.
Corticosteroids
Topical, injected, or selected systemic corticosteroids may reduce local immune activity.
Route and suitability depend on the individualContact immunotherapy
Specialist-applied treatment may be considered for more extensive or persistent disease.
Requires medical supervisionJAK inhibitors
Prescription immune-modulating medicines are available for selected people with severe alopecia areata.
Screening, monitoring, risks, and age criteria matterGrowth and cosmetic support
A clinician may use growth stimulants alongside immune-directed care; camouflage, wigs, brows, and counseling can also support quality of life.
Support is part of care—not an afterthoughtHair may regrow spontaneously or with treatment, sometimes initially fine or white. Regrowth does not guarantee that another episode will not occur.
Think in patterns over time—not promises.
A limited patch may regrow and never recur.
Hair may regrow while a new patch appears elsewhere.
Some areas remain active or progress despite treatment.
A smaller group develops total scalp or wider body-hair loss.
Early evaluation matters when the pattern is changing quickly.
Arrange prompt medical assessment for rapid expansion, eyebrow or eyelash loss, extensive shedding, nail changes, scalp pain or inflammation, signs of infection, hair loss in a child, or a major effect on emotional wellbeing.
Find a verified trichologist →Alopecia areata, clearly explained.
Is alopecia areata contagious?+
No. Alopecia areata is an autoimmune condition and cannot be passed from one person to another.
Can stress cause alopecia areata?+
Stress or illness may precede an episode in some susceptible people, but many cases have no obvious trigger. The condition is not simply caused by stress.
Will the hair grow back?+
Regrowth is possible because the follicles are usually not permanently destroyed, but the course is unpredictable. Hair can regrow fully, partially, or fall out again later.
Can it affect more than the scalp?+
Yes. Alopecia areata may affect the beard, eyebrows, eyelashes, or other body hair. Nail pitting or roughness can also occur.
Is there a cure?+
There is currently no permanent cure, but treatment can reduce immune activity and help stimulate regrowth in some people.
Who should evaluate it?+
A dermatologist should diagnose suspected alopecia areata and direct medical treatment. A qualified trichologist can document the pattern, support monitoring, and coordinate referral.
Compare sudden patches with other patterns of hair loss.
The next guides can help distinguish autoimmune loss from diffuse shedding and mechanical damage.
Medical review notes
This guide retains the current Trichology.com explanation of autoimmune follicle attack, patchy and diffuse loss, totalis and universalis, diagnosis, associated conditions, medical treatment, and unpredictable regrowth, reorganized for clearer consumer use.
Medical disclaimer: This content is educational and is not a diagnosis or substitute for care from a qualified health professional.