
Frontal fibrosing alopecia
A slowly receding band across the forehead and temples—especially with eyebrow loss, redness, scale, itching, or burning—can signal inflammation that permanently damages follicles.
Educational guide · Suspected scarring alopecia requires dermatologist-led diagnosis and care

What is frontal fibrosing alopecia?
Frontal fibrosing alopecia—FFA—is an inflammatory scarring alopecia that usually recedes the frontal and temporal hairline and frequently affects the eyebrows.
- It belongs to the lichen planopilaris spectrum.
- Symptoms can be obvious, subtle, or absent.
- The priority is preventing additional permanent loss.

FFA can extend beyond the forehead.
The hairline often recedes as a smooth, pale band, but the brows, temples, sideburns, and other hair-bearing areas can provide equally important clues.
Frontal and temporal margin
Band-like recession may leave isolated “lonely hairs” ahead of the new hairline.
Eyebrows and sideburns
Partial or complete eyebrow loss may appear early; sideburn density can also decline.
Face and body
Some people develop facial papules or reduced hair on the arms, legs, underarms, or pubic area.
Inflammation may be active at the newest edge.
The appearance varies by stage and skin tone. A photograph cannot determine whether disease is active.
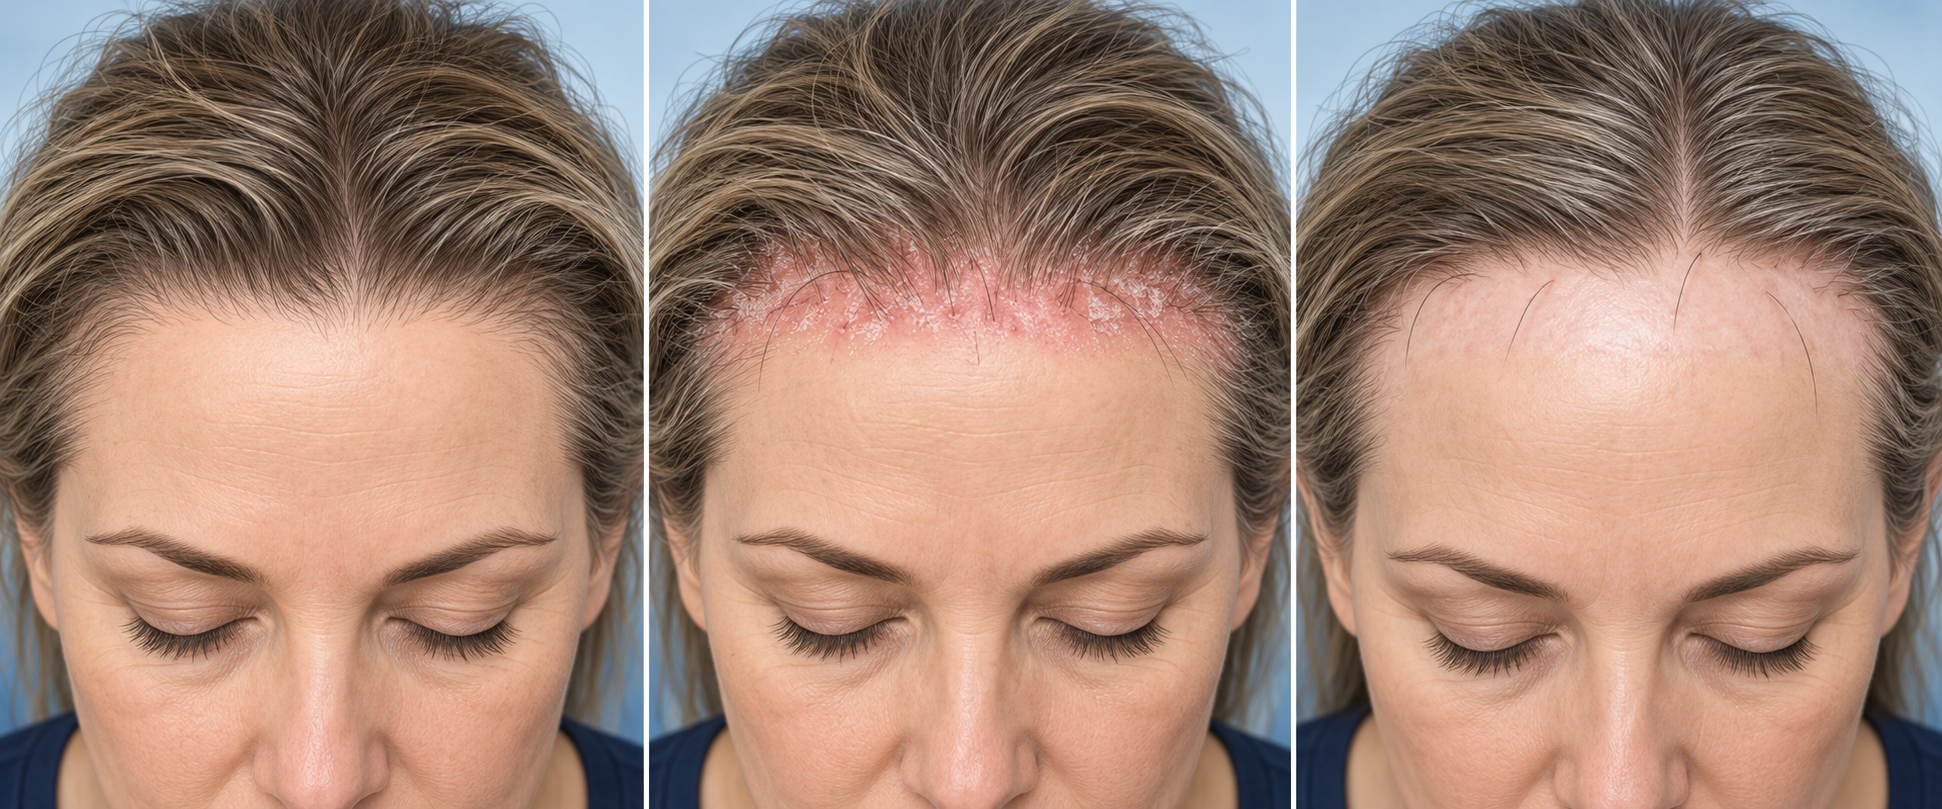
Subtle recession or brow loss
The first change may be easy to overlook or mistaken for ordinary aging or pattern thinning.
Redness and scale around hairs
Perifollicular inflammation, itching, burning, tenderness, or facial papules may occur.
Smooth skin without openings
The receded zone may look pale or shiny, with isolated hairs and absent follicular openings.
Eyebrow and skin changes belong in the same assessment.
FFA may involve more than scalp hair. A complete examination can identify features that separate it from ordinary pattern thinning or traction.
- Partial or complete eyebrow thinning
- Small facial papules, especially near the temples
- Redness or scale around individual hairs
- Itching, burning, pain, tenderness—or no symptoms
- Loss of sideburn, facial, or body hair in some people
It is most common after menopause—but not exclusive to one group.
Postmenopausal women
The condition is diagnosed most often in this group, but that pattern should not become a diagnostic shortcut.
Younger women and men
Premenopausal women and men can develop FFA, and the condition may be overlooked when it appears outside the typical demographic.
Presentation can be less obvious
Redness may be subtler in darker skin, and traction or androgenetic alopecia can coexist and complicate recognition.
Pattern, magnification, and sometimes biopsy work together.
Map and measure
Document the frontal and temporal margin, brows, sideburns, symptoms, facial or body changes, and rate of progression.
Trichoscopy
Magnification may show missing openings, perifollicular scale or redness, white scarred areas, and lonely hairs.
Biopsy when needed
A dermatologist may sample an active margin to distinguish FFA from other scarring and non-scarring causes.
A verified trichologist can document the pattern and coordinate referral. Medical diagnosis, biopsy, prescription treatment, and inflammatory-disease management require an appropriately licensed healthcare professional.
Frontal recession is not automatically FFA.
Traction alopecia
Repeated hairstyle tension often affects the margins and may coexist with FFA.
Androgenetic alopecia
Pattern thinning miniaturizes follicles without initially producing a smooth scarred band.
Alopecia areata
A non-scarring autoimmune pattern can affect the hairline and eyebrows but has different close-up signs.
The goal is stability—not restoration of scarred follicles.
No single treatment works uniformly. A dermatologist tailors care to activity, extent, symptoms, coexisting hair loss, health history, and risk.
Reduce local inflammation
Prescription topical or injected anti-inflammatory medicines may be considered for an active margin.
Requires medical selectionConsider systemic therapy
Progressive disease may require oral anti-inflammatory, immune-modulating, or other specialist-directed treatment.
Monitoring and risks varyAddress overlapping loss
Androgenetic or traction-related loss can coexist and may require a separate treatment strategy.
Each contributor is individualTrack stability
Repeat photographs, measurements, symptoms, and trichoscopy help reveal continued recession.
Compare consistently over timeDo not start, stop, or change prescription treatment based on this guide. Hair transplantation is considered only after prolonged specialist-confirmed stability; recurrence and reduced graft survival remain possible.
A changing hairline plus eyebrow or scalp symptoms should not be dismissed.
Arrange dermatology assessment for progressive frontal or temporal recession, eyebrow loss, perifollicular redness or scale, isolated hairs in a smooth band, facial papules, or persistent itching, burning, pain, or tenderness.
Find a verified trichologist →Frontal fibrosing alopecia, clearly explained.
Is frontal fibrosing alopecia permanent?+
Hair cannot regrow from follicles that have been fully destroyed and replaced by scar tissue. Treatment aims to suppress active inflammation and preserve follicles that remain.
Does FFA affect only postmenopausal women?+
No. It is most often recognized in postmenopausal women, but premenopausal women, men, and people of all ethnic backgrounds can develop it.
Can eyebrow loss come before scalp recession?+
Yes. Eyebrow thinning or loss may be an early feature and can precede an obvious change in the frontal hairline.
Is FFA the same as lichen planopilaris?+
FFA is generally considered a patterned form within the lichen planopilaris spectrum. The band-like frontal and temporal distribution distinguishes its clinical presentation.
Can sunscreen or facial products cause FFA?+
Associations with leave-on facial products have been studied, but an association does not prove causation. The cause remains unclear, and stopping sun protection without medical advice is not recommended.
How is progression measured?+
Standardized photographs, measurements from stable facial landmarks, eyebrow assessment, symptoms, and trichoscopy help show whether the hairline is changing.
Can hair transplantation restore the hairline?+
It may be considered only after a specialist confirms prolonged disease stability. Recurrence and reduced graft survival are possible, so results cannot be guaranteed.
Medical review notes
This guide preserves the current Trichology.com foundation—pattern, eyebrow and body-hair involvement, LPP relationship, causes under study, examination, trichoscopy, biopsy, differential diagnosis, treatment categories, monitoring, and prognosis—while making early recognition clearer.
Medical disclaimer: Educational information only; not a diagnosis or substitute for qualified medical care.
Compare FFA with related scarring patterns.
These guides help distinguish an inflammatory frontal pattern from other causes of a changing hairline.