
Botox &
Hair Loss
Proposed mechanisms, early clinical research and the limits of an emerging intervention

 William Gaunitz, WTSClinical Trichologist · Expert Reviewer

Emerging procedural research
Use these questions to navigate the complete physician-authored review below.
The review explains proposed pathways involving muscle tension, perfusion and the follicular environment.
Read this section →A mechanical hypothesis is explored as a possible contributor, with its clinical limits kept visible.
Read this section →Complete production article and literature cited.
Botox and Hair Loss: A Review of the Literature
Key Takeaways
- Botox may improve scalp circulation and follicular oxygenation through localized muscle relaxation and reducing tension around hair-bearing regions.
- Early clinical studies demonstrate measurable increases in hair count, density, and anagen-to-telogen ratio in patients with androgenetic alopecia (AGA).
- Mechanistic pathways may involve decreased local dihydrotestosterone (DHT) activity, reduced neuroinflammatory signaling, and enhanced microvascular perfusion.
- Evidence is preliminary, with small sample sizes, variable methodologies, and limited long-term follow-up.
- Best utilized as an adjunctive treatment within a comprehensive trichology program.
Introduction
Botulinum toxin type A, known by its trade name Botox, is one of the most widely used neuromodulators in aesthetic and medical dermatology.
While its best-known applications involve the temporary relaxation of facial muscles to reduce wrinkles, emerging research has uncovered potential scalp and hair-related benefits.
Over the past two decades, anecdotal and clinical observations have raised a compelling question: Could Botox help prevent or even reverse certain types of hair loss?
This interest stems from a growing understanding of the neurovascular and muscular influences on scalp physiology. Hair follicles are highly sensitive micro-organs that rely on consistent perfusion, oxygenation, and hormonal balance.
However, as enthusiasm for Botox grows across dermatologic and trichology circles, so too does the need for critical evaluation. Published studies vary widely in design, methodology, and outcomes, and the exact mechanisms behind any observed improvements remain under investigation.
By examining biological mechanisms, clinical evidence, and ongoing controversies, we aim to distinguish fact from fiction, clarifying where Botox may genuinely fit within modern trichology practice.
The Biological Basis: Scalp Tension and Hair Follicle Health
The connection between scalp muscle tension and hair loss has gained increasing attention in trichology research, particularly in the context of androgenetic alopecia (AGA).
The scalp contains several small muscle groups; the occipitofrontalis, temporalis, and galea aponeurotica, that can exert subtle but chronic tension across the scalp surface.
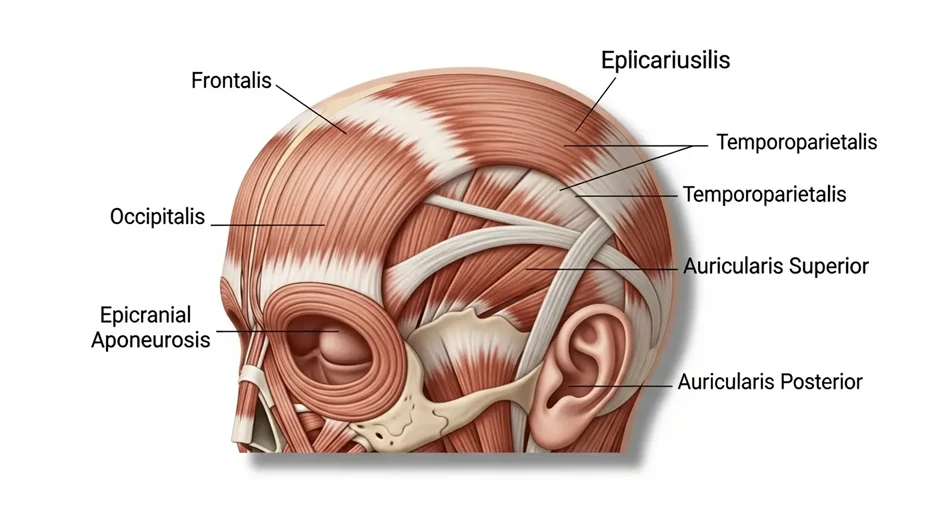
Figure 1. Muscles of the Scalp1
Over time, this persistent contraction may contribute to microvascular compression, reducing local oxygenation and nutrient delivery to hair follicles. As hair follicles are highly metabolic structures, even minor reductions in blood flow can disrupt the anagen (growth) phase and promote follicular miniaturization2.
Botulinum toxin (Botox) acts by blocking acetylcholine release at the neuromuscular junction, temporarily relaxing targeted muscles3.
When injected into the scalp, this relaxation is hypothesized to reduce mechanical pressure on perifollicular vessels, enhancing microcirculation and restoring nutrient and oxygen flow to the hair matrix.
Improved perfusion also helps remove metabolic byproducts and local inflammatory mediators, creating a more favorable environment for follicular health4.
Enhanced oxygen availability may indirectly influence 5α-reductase activity, the enzyme responsible for converting testosterone into dihydrotestosterone (DHT), a key driver of AGA.
Hypoxic tissue conditions have been linked to upregulated DHT synthesis, so restoring normal oxygenation could modulate this pathway5.
This proposed mechanism contrasts sharply with conventional treatments such as finasteride, which systemically inhibits 5α-reductase6, and minoxidil, which acts as a topical vasodilator7.
Botox’s approach is mechanical and physiologic rather than pharmacologic, targeting the root cause of scalp tension and offering a novel adjunctive strategy for promoting hair regrowth and scalp health.
Clinical Evidence: What the Studies Show
The clinical exploration of Botox for androgenetic alopecia (AGA) began with a landmark pilot study by Freund and Schwartz, which first introduced the concept of scalp muscle relaxation improving hair growth.
In this study, 40 men with AGA received intramuscular injections of botulinum toxin type A (150 units total) distributed across the frontal, temporal, and occipital regions8.
After 48 weeks, 75% of participants demonstrated visible regrowth, with mean hair counts increasing by approximately 18% and a notable improvement in the anagen-to-telogen ratio. The authors proposed that reduced scalp tension and enhanced blood flow lowered local DHT levels, promoting follicular recovery.
Subsequent trials have attempted to replicate and refine these findings. A pilot study assessed 10 men with AGA who received 150 units of Botox evenly over 30 scalp injections sites. 8 out of 10 men exhibited excellent responses in hair growth, and only one showed no difference at all based on photographic results9.
Smaller case series and open-label studies have explored variable dosages (100–300 units) and modified injection mapping, noting consistent improvements in hair thickness, scalp pliability, and perceived fullness10.
A few exploratory studies have even reported benefits in conditions beyond AGA, including:
- Telogen effluvium
- Seborrheic dermatitis
- Tension-related shedding
where scalp microcirculation and inflammation play contributory roles11.
Although Botox exerts measurable improvements in scalp health and hair density, multicenter, double-blind RCTs are required to establish standardized treatment protocols and confirm reproducibility across diverse patient populations.
Mechanistic Pathways Beyond Muscle Relaxation
Beyond its neuromuscular blockade, botulinum toxin appears to influence local inflammatory and neuropeptide signaling, creating a microenvironment more conducive to hair follicle function and regeneration.
One key area of interest involves neuropeptide modulation, particularly the downregulation of Substance P12, which has been implicated in neurogenic inflammation leading to13:
- Follicular stress
- Microvascular constriction
- Perifollicular immune activation
By suppressing their release, Botox reduces pro-inflammatory cytokines such as IL-6 and TNF-α14, which could mitigate chronic inflammation that accelerates follicular miniaturization and hair cycle disruption.
Additionally, Botox can improve cutaneous blood flow and endothelial function, possibly through nitric oxide–mediated vasodilation15. This could enhance nutrient and oxygen delivery to the scalp’s microvasculature, complementing the mechanical benefits of muscle relaxation.
However, it is important to emphasize that these non-muscular mechanisms remain theoretical. Most supporting evidence comes from small experimental models or extrapolations from other tissues.
Robust histological studies are still needed to confirm Botox’s direct molecular impact on hair follicle biology to determine whether these effects are independent or synergistic with its neuromuscular action.
Botox and Hair Loss: Emerging Evidence
While most emerging literature explores Botox as a potential adjunct therapy for androgenetic alopecia, a small but important body of evidence suggests that Botulinum toxin type A (BTX-A) may, in rare cases, contribute to hair loss.
A 2016 observational report detailed five women (mean age ~ 53) who developed progressive frontal hairline recession after years of repeated BTX-A injections specifically for forehead wrinkles (treatment duration ranged anywhere from 1–10 years).
Trichoscopy showed:
- Miniaturized vellus and intermediate hairs
- Preserved follicular ostia
- No scarring
differentiating this phenomenon, named botulin-induced frontal alopecia (BIFA), from frontal fibrosing alopecia.
Although the mechanism is unclear, proposed pathways include altered neuropeptide signaling (e.g., substance P), or disrupted autonomic input to the follicle, potentially impairing the hair cycle.
Notably all cases demonstrated gradual thinning, suggesting a dose- or exposure-dependent effect. This underscores the need for clinicians to monitor hairline changes in long-term cosmetic Botox users16.
Limitations and Controversies in Literature
Despite growing enthusiasm for the use of Botox as a novel intervention for hair loss, the scientific evidence remains preliminary and varied. One of the biggest challenges lies in the lack of standardized treatment protocols across published studies.
Injection depth, anatomical targeting, and dosing vary widely, from 100 to 300 units per session, applied at anywhere from 20 to 30 scalp sites. Follow-up durations often range from 3 to 12 months, leaving long-term efficacy and durability of results largely uncharacterized.
Many clinical trials also rely on subjective endpoints such as patient-reported satisfaction or visual improvement, rather than objective measures like trichoscopy or phototrichogram-based density counts. This introduces potential observer bias.
Safety data, though generally favorable, are limited to small cohorts. While most participants report only mild, transient discomfort, data on repeated or long-term scalp injections is lacking.
Botox used explicitly for forehead wrinkles (not for scalp regrowth) should also be monitored for rare cases of hair loss.
Overall, the literature presents a promising yet inconsistent picture: Botox appears safe and beneficial for select patients, but methodological disparities and a lack of large, controlled, long-term trials mean its precise role remains to be definitively established.
Clinical Implications: Integrating Botox in Trichologic Practice
Within modern trichology, Botox is emerging as a potential adjunctive therapy rather than a replacement for established hair loss treatments.
Its mechanism: relieving scalp tension, improving vascular perfusion, and modulating inflammation, makes it most suitable for patients exhibiting mechanical scalp strain, vascular insufficiency, or stress-related shedding.
Candidates who describe scalp tightness, reduced pliability, or discomfort along thinning zones tend to show the most benefit.
In practice, Botox can be strategically integrated with other evidence-based modalities such as:
- Minoxidil
- Platelet-rich plasma (PRP)
- Low-level laser therapy (LLLT)
When combined, these treatments address multiple pathophysiologic dimensions: vascular, inflammatory, and hormonal, creating a synergistic environment for follicular recovery and prolonged anagen phase maintenance.
Clinicians should emphasize to patients that Botox offers temporary improvement, with results typically lasting three to six months before requiring maintenance sessions.
Appropriate expectations, individualized dosing, and precise anatomic mapping are critical for safety and efficacy.
FAQs
1. Can Botox really help regrow hair?
Current evidence suggests that Botox can support hair regrowth in some individuals by improving scalp blood flow and reducing muscular tension around hair follicles.
Its benefits are best seen when used as part of a broader treatment plan.
2. How does Botox differ from finasteride or minoxidil in treating hair loss?
Unlike finasteride, which inhibits DHT production, or minoxidil, which prolongs the growth (anagen) phase, Botox works mechanically by relaxing scalp muscles, improving oxygenation, and potentially reducing inflammation.
3. Are results permanent or do they wear off?
Botox effects are temporary, typically lasting three to six months. Maintenance sessions are required for sustained improvement.
4. What are the risks or side effects of scalp Botox?
Botox is generally well tolerated. Side effects are mild and transient, including minor pain at injection sites, temporary scalp tenderness, or mild headaches. Serious complications are rare when performed by a trained medical provider.
5. Can Botox cause hair shedding or damage follicles?
There is no evidence that properly administered Botox damages follicles or induces hair shedding.
6. How many sessions are needed, and how often?
Most protocols involve one treatment session every 3–6 months, depending on response and scalp condition. Some patients notice improved density or reduced shedding after the second session.
7. Who is the ideal candidate for Botox hair restoration therapy?
Ideal candidates are individuals experiencing androgenetic alopecia with scalp tightness, poor circulation, or stress-related tension, rather than isolated hormonal or nutritional causes of hair loss.
8. Is Botox part of the Gaunitz Trichology Method?
Yes, Botox can be integrated within the Gaunitz Trichology Method as a supportive therapy for improving scalp perfusion and tension reduction.
However, it is not used in isolation: it complements metabolic, hormonal, and nutritional optimization as part of a comprehensive, science-based approach to hair restoration.
References
1. Expert HT. Understanding the Scalp Muscle: Anatomy, Function & Health Benefits. September 6, 2025. Accessed November 9, 2025. https://drranairfan.com/understanding-the-scalp-muscle/
2. English RS. A hypothetical pathogenesis model for androgenic alopecia: clarifying the dihydrotestosterone paradox and rate-limiting recovery factors. Medical Hypotheses. 2018;111:73-81. doi:10.1016/j.mehy.2017.12.027
3. Padda IS, Tadi P. Botulinum Toxin. In: StatPearls. StatPearls Publishing; 2025. Accessed November 9, 2025. http://www.ncbi.nlm.nih.gov/books/NBK557387/
4. Hussein RS, Dayel SB, Abahussein O. Botulinum Toxin A for Hair Loss Treatment: A Systematic Review of Efficacy, Safety, and Future Directions. JPRAS Open. 2023;38:296-304. doi:10.1016/j.jpra.2023.09.006
5. Park C, Kim Y, Shim M, Lee Y. Hypoxia enhances ligand-occupied androgen receptor activity. Biochemical and Biophysical Research Communications. 2012;418(2):319-323. doi:10.1016/j.bbrc.2012.01.019
6. Finasteride – StatPearls – NCBI Bookshelf. Accessed November 9, 2025. https://www.ncbi.nlm.nih.gov/books/NBK513329/
7. Patel P, Nessel TA, Kumar D D. Minoxidil. In: StatPearls. StatPearls Publishing; 2025. Accessed November 9, 2025. http://www.ncbi.nlm.nih.gov/books/NBK482378/
8. Freund BJ, Schwartz M. Treatment of Male Pattern Baldness with Botulinum Toxin: A Pilot Study. Plastic and Reconstructive Surgery. 2010;126(5):246e. doi:10.1097/PRS.0b013e3181ef816d
9. Singh S, Neema S, Vasudevan B. A Pilot Study to Evaluate Effectiveness of Botulinum Toxin in Treatment of Androgenetic Alopecia in Males. J Cutan Aesthet Surg. 2017;10(3):163-167. doi:10.4103/JCAS.JCAS_77_17
10. English Jr. RS, Ruiz S. Use of Botulinum Toxin for Androgenic Alopecia: A Systematic Review. Skin Appendage Disord. 2022;8(2):93-100. doi:10.1159/000518574
11. Perez SM, AlSalman SA, Nguyen B, Tosti A. Botulinum Toxin in the Treatment of Hair and Scalp Disorders: Current Evidence and Clinical Applications. Toxins (Basel). 2025;17(4):163. doi:10.3390/toxins17040163
12. Matak I, Tékus V, Bölcskei K, Lacković Z, Helyes Z. Involvement of substance P in the antinociceptive effect of botulinum toxin type A: Evidence from knockout mice. Neuroscience. 2017;358:137-145. doi:10.1016/j.neuroscience.2017.06.040
13. Siebenhaar F, Sharov AA, Peters EMJ, et al. Substance P as an immunomodulatory neuropeptide in a mouse model for autoimmune hair loss (alopecia areata). J Invest Dermatol. 2007;127(6):1489-1497. doi:10.1038/sj.jid.5700704
14. Ham HJ, Yeo IJ, Jeon SH, et al. Botulinum Toxin A Ameliorates Neuroinflammation in the MPTP and 6-OHDA-Induced Parkinson’s Disease Models. Biomol Ther (Seoul). 2022;30(1):90-97. doi:10.4062/biomolther.2021.077
15. Hu L, Feng Y, Liu W, Jin L, Nie Z. Botulinum toxin type A suppresses arterial vasoconstriction by regulating calcium sensitization and the endothelium-dependent endothelial nitric oxide synthase/soluble guanylyl cyclase/cyclic guanosine monophosphate pathway: An in vitro study. Exp Biol Med (Maywood). 2019;244(16):1475-1484. doi:10.1177/1535370219878143
16. Di Pietro A, Piraccini BM. Frontal Alopecia after Repeated Botulinum Toxin Type A Injections for Forehead Wrinkles: An Underestimated Entity? Skin Appendage Disord. 2016;2(1-2):67-69. doi:10.1159/000448380